

White-label telehealth with the medical director already attached.
The storefront is the easy part. The medicine behind it is not. Your brand and your domain in front, and behind them a professional entity, an already credentialed provider network and a good faith exam process that an order does not get past until a provider licensed in your patient's state has written the prescription.
What the platform includes · Use your own front end
Most of this market sells you half of this and leaves you to find the other half yourself. There is no second vendor to hire and no pharmacy relationship to go build before you can open.
The rule set that decides which states you can sell in. All 51, each one cited.
This is the rule set the platform routes on, all 51 jurisdictions, each one cited. It decides whether an order can complete asynchronously, whether it needs live video, and whether it can go through at all.
Most vendors tell you they handle state rules. This is the part where you check.
Five jurisdictions come back hedged, because the rule there is genuinely unsettled and we would rather show you that than round it off. Louisiana comes back as a no: weight management does not route there at all. A vendor that will not show you the states where it declines your order is showing you a feature list.
The verdict above covers weight management. It does not extend to IV therapy, which is ordered and supervised on its own terms.
Tex. Occ. Code 111.005, 111.005(a)(3)
Read September 19, 2026, from a 51-jurisdiction regulatory survey. Rules change. Nothing here is a substitute for your own counsel.
Bring your target states to the call. Most calls start with this list.

An order that comes in the front has to be lawful by the time it goes out the back.
Most telehealth platforms stop at checkout. They will take a card, build a funnel and hand you a dashboard. What happens between the moment a customer clicks buy and the moment a medication ships is somebody else's problem.
That gap is the entire regulated part of a direct-to-consumer health business. It is what a state medical board asks about, what a compounding pharmacy refuses to fill without, and what a buyer's counsel spends a month on during diligence. MDside AI is built inside that gap rather than around it.
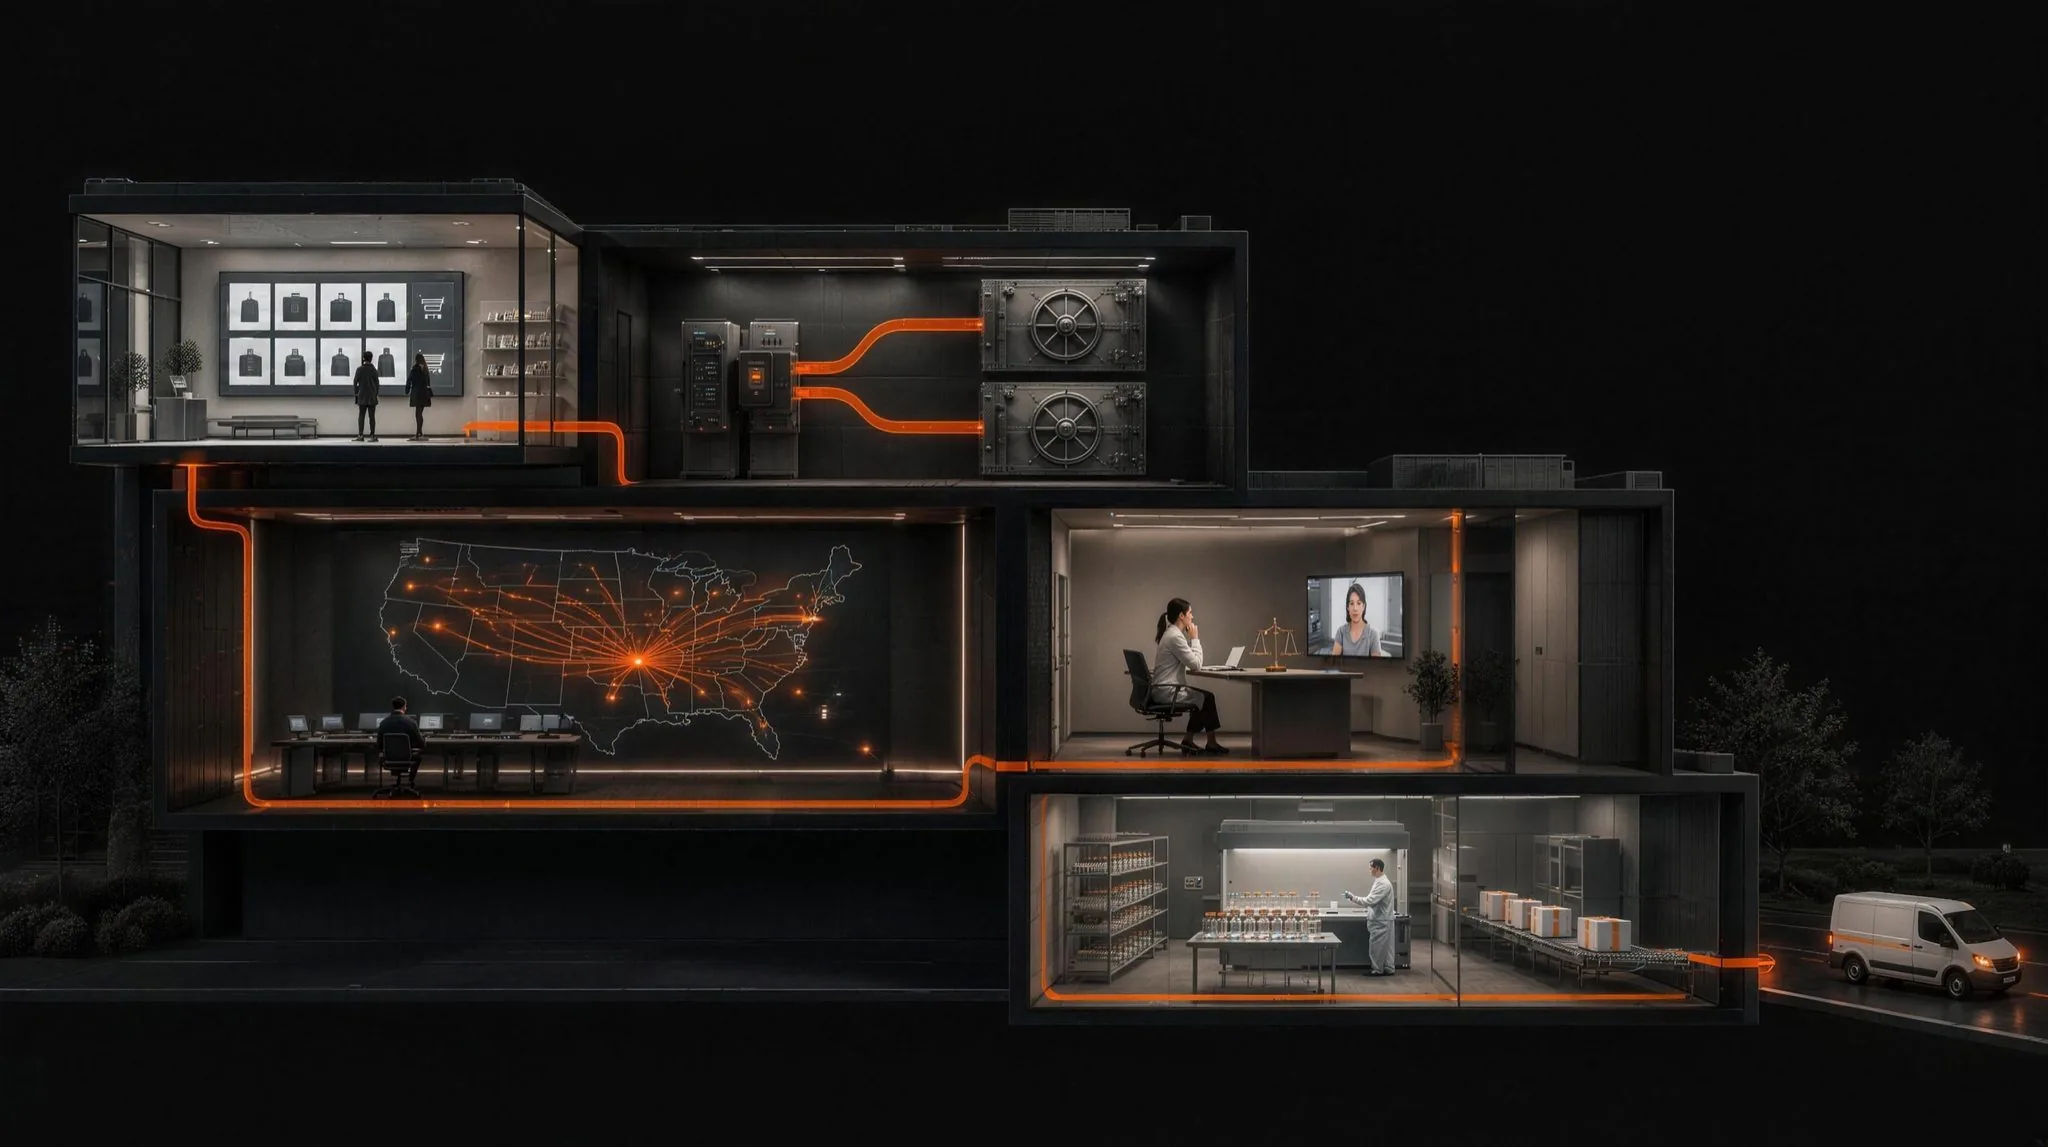
What happens between buy and ship
-
01
Your storefront
A white-labeled telehealth site under your name, your domain and your catalog. It does not say MDside on it. The configuration is ours. The brand is yours.
-
02
Payments that land in the right entity
Two fees, two entities. Stripe Connect routes the professional fee to the account of the professional entity and bills the management fee under the services agreement, from the first transaction. That is a structural decision rather than an accounting cleanup you do later.
-
03
Routing by the patient's state
Every order goes to a provider licensed where the patient is sitting. This step decides which states you can open, and you can check any of the 51 above.
-
04
A good faith exam
A licensed provider weighs the request and can decline it. Some states accept that asynchronously and some require live video. The routing already knows which.
-
05
Fulfillment against a prescription
A 503A pharmacy fills a patient-specific prescription written by the provider who performed the exam. Order, exam, prescription, fill, in that order, with a record at each step.
Five stages, one system, one record that carries through all of them. The sequence is the product. Background reading on the stages that carry the most risk: fixed fee vs percentage of revenue, licensure follows the patient, good faith exams by telehealth, and 503A vs 503B sourcing.

Anyone can ship a website. The hard part is the licensed provider who has to look at the order before it becomes a prescription.

One console for the whole chain
Approvals, orders, offerings, intake and the storefront in one place. Every request carries the state it came from and the provider who owns it, because that pair decides whether the encounter is defensible.
Pennsylvania routes to video because asynchronous is not addressed at 49 Pa. Code 16.92. Louisiana declines weight management by telemedicine under LAC 46:XLV.7513(C)(2). The console does not ask your staff to remember that.
| Patient | State | Request | Status |
|---|---|---|---|
| A. Whitfield | TX | Weight | Awaiting |
| K. Underwood | CA | Weight | Approved |
| M. Okonkwo | NY | Weight | Approved |
| J. Barrett | PA | Weight | Awaiting |
| S. Nakamura | LA | Weight | Declined |
Everything on the operator side, already built
The exam and the prescription are the hard part, but a patient still has to buy, answer an intake, get a refill and find their order. MDside AI runs all of that under your brand, on the same record the provider works from, so nothing gets re-keyed between a checkout and a chart.
Offerings are switched on for you by MDside with the intake and the protocol already attached. You set the price, share the checkout link, and the rest of the chain runs from there.
- A patient portal on your domainOne domain you own serves the storefront, the patient portal and every checkout link. Order emails come from your domain too, not ours. Patients see their orders, plans and messages in one place.
- Intake that screens before a provider sees itA managed question bank asked at every checkout, with screening built in: some answers disqualify, others flag the request for the provider. Add your own follow-up questions under any of ours, with no forms to build. Need a patient to finish one before a visit? Text them the link and they complete it on their phone.
- Card held, not charged, until a provider approvesThe card is authorized at checkout and captured only when a licensed provider approves. A decline releases the hold. Patients are never billed for a prescription that was not written.
- Treatment plans that renew on their ownApproved plans rebill on schedule. Patients get a reminder 1 to 14 days before each renewal with the date, the amount and a link to pause or cancel, then an email when the next dose goes to the pharmacy, when it ships and when it is delivered.
- Leads from abandoned checkoutsAnyone who starts a checkout and does not finish lands in a lead queue with their consent status and how far they got. Run an automatic follow-up sequence, work them by hand, or export to CSV.
- Promotions, analytics and your own teamRun coupons and categories without a developer. See visitors, top pages and referrers, with bot and AI-crawler traffic counted separately. Staff get their own logins and alert settings, and an alert never contains the message itself, only a link back to the secure thread.
The chart, the labs and the supply chain behind it
A storefront is only as dependable as what it hands off to. The medical record, the lab results, the pharmacy and the card processor all sit inside MDside AI, and where one of them can fail there is a second one ready, so a single vendor's bad day does not reach your patients.
None of it changes who decides. The record is built for the provider, and the provider still makes every clinical call.
- A full medical record for every patientNotes, prescriptions, intake answers, messages and history in one chart that the provider works and prescribes from, not an order log with a notes field bolted on.
- Lab results you can read as a trendEach patient's results are plotted over time, so a provider sees which way a value has been moving instead of a single number. Lab orders and results connect with Quest Diagnostics, Labcorp and Access Medical Laboratories.
- More than one pharmacy behind every orderOrders can be routed between several partner pharmacies. When one is backordered or slow on a product, the order goes to another and the patient's dose does not wait on it.
- Payments that keep running in an outageCharges are spread across more than one card processor. If one of them goes down, payments move to another and checkout stays open.
- AI drafts, the provider decidesEvery request arrives with a drafted SOAP note and triage, so the provider spends their time on the decision rather than the paperwork. The approval itself is always a licensed provider's call.
- Help getting LegitScript certifiedMDside is LegitScript certified and has a partnership with LegitScript. Your application is prepared against the same pieces LegitScript looks at: the professional entity, the pharmacies, the labs and the protocols. The decision and its timing stay with LegitScript.
Use our storefront, your own, or both
Some operators want a store that works on day one. Others already have a site, an app or an EMR and only need the regulated part behind it. MDside AI runs either way. Sell through the hosted storefront and checkout links, or keep your own front end and send requests to the API. The provider network, the state routing and the good faith exam are the same underneath.
Build against a sandbox first. Test keys run the full flow, nothing reaches a provider and nothing bills.
- A REST API for the whole loopEndpoints for intake, submitting a request, polling its status, your live product list and the patient portal, with every route and error documented.
- Webhooks for every decisionGet the provider's decision and order updates pushed to your system the moment they happen, or poll if you prefer.
- A sandbox that cannot hurt anyoneTest keys run every endpoint end to end, from the docs page or from Postman. No real provider sees a test request and no card is charged.
- Set up with an AI coding toolOne endpoint returns an integration guide written for your clinic at the moment you call it: your plan, your products, which states they cover and a go-live checklist of what is still missing. Point Claude Code, Cursor or Codex at it and it builds against the current contract, not a stale copy.
- Logs you can readEvery API call for the last 30 days, with status and timing, in the console. Patient data never appears in a log, only ids, statuses and timestamps.
 MDside×

Every patient gets an answer on the first ring
The 9pm call about a refill. The same insurance question for the fourth time before lunch. The text asking to move Thursday. Most practices lose those to voicemail. MDside AI answers all of them, on chat, phone, text and email, in the patient's own language, under your brand.
That front office is built by Clarky, a co-owner of MDside AI. Clarky runs the conversation. MDside runs the medicine. Anything that needs clinical judgment goes to a licensed provider, and the assistant never approves, prescribes or declines a thing.
- A phone line that picks upNatural speech, one ring, no phone tree, no hold music. The request is routed to the right queue before the patient would have reached a voicemail box.
- Chat, text and email in one brainThe same knowledge and the same calendar on every channel. Texts come from your number. Routine email is sorted and answered before your team logs in.
- Booking inside the conversationReal availability, picked in the chat or over the phone. Confirmations and reminders go out on their own, so the no-shows stop before Monday.
- A human can step in mid-sentenceEvery chat, call, text and email lands in one thread per patient, with full context. Your staff takes over the moment they are needed.
- HIPAA, with the paperwork to prove itClarky is HIPAA compliant and signs a BAA with MDside, and every client signs a BAA with us, so the chain is covered end to end. Encrypted at rest and in transit, role-based access, and conversations are never used to train outside models.

Two vendors who have never spoken
The difficulty is not the software. It is that the two halves are normally bought separately. Most platform companies have no medical director. Most medical groups have no storefront. The seam between them is where the orders, the records and the liability fall through.
Here, the platform and the professional entity are built to work together from the start, so the handoff is a function call rather than an email chain. MDside is a PC-MSO run by a physician, and clinical decisions sit with licensed providers in fact, not only in the agreement. The result is the thing a buyer's counsel is looking for later: records that match behavior, fees that match the agreement, protocols with approval dates. That is what diligence actually finds.
Two questions separate this category quickly, whichever vendor you are evaluating. Who performs the good faith exam, holds the professional entity and answers a state board. And what sets your launch date, because that answer tells you whether the clinical side already exists or gets assembled after you sign.

What MDside AI does not do
Five things we will not do. Each one is a decision, and each one is somewhere this market usually promises you more than it can defend.
- It does not decide who gets treated. A licensed provider does, and that provider can decline. A platform that cannot say no is not performing an exam.
- It does not make you compliant on its own. Your entity structure, your licensure and your protocols still have to be right, and those sit in the clinical layer, not the software.
- It does not replace your counsel. We will tell you what we read the rule to be and show you the citation by number. Your lawyer still signs off.
- It does not ship you a shelf of ready stock. 503A compounding is patient-specific and runs against a prescription written for a named patient. A vendor offering you standing office stock is handing you the part of this a pharmacy board looks at first. Where office use is lawful in your state it is a conversation with your pharmacy, and it sits outside the platform. See office-use compounding by state.
- It does not promise a controlled-substance workflow that outlives the rules. Telehealth prescribing of controlled substances runs on federal flexibilities with an expiry date. See what happens January 1, 2027.
What operators ask before they sign
How is MDside AI different from the others?
MDside is a physician-led PC-MSO first and a platform second. The medical director, the professional entity, the already credentialed provider network and the good faith exam process sit with the professional entity, and MDside AI is the technology that serves it.
Ask any vendor you are evaluating who holds the professional entity, who performs the exam, whether that person can decline, and who answers a state board. The answers separate the category quickly.
What actually sets the launch date?
Three things, and none of them is the website: whether a professional entity already exists in the state, whether a provider is already licensed where your patients are, and whether approved, version-dated protocols exist for what you are selling.
The provider network is already credentialed and already licensed across most of the country, so the second one is usually answered before you ask. The professional entity is state by state: in some states one already exists, and in others forming or qualifying it is the long pole. Ask us which applies to the states you want and you will get the list. No vendor can compress a state licensing board, and a launch that skips approved protocols is not fast, it is early. When a platform quotes you a date, ask which of the three it is counting.
Who performs the good faith exam?
A physician, nurse practitioner or physician assistant licensed in the state where the patient is located at the time of the encounter. Not a medical assistant, not an RN, not a form. See good faith exams.
That provider can decline. A workflow with no decline path is not an exam, and it is the first thing that fails when somebody actually reads the chart.
Can the exam be asynchronous?
It depends on the state and on the product. Store-and-forward encounters are accepted in most states for non-controlled medications. Several states prohibit them, do not address them, or require a real-time exchange. A static question set with no adaptive branching is not a defensible encounter anywhere.
Routing has to be gated by state, product and modality together. See asynchronous telehealth by state.
Can I use my own website or app instead of your storefront?
Yes. You can sell through the hosted storefront and checkout links, connect your own front end through the API, or run both. Either way the order goes through the same state routing and the same good faith exam by a provider licensed where the patient is.
Integration starts in a sandbox with test keys, where nothing reaches a provider and nothing is charged.
Do patients get a portal?
Yes, on your domain and under your brand. Patients see their orders, treatment plans and messages there, and get emails when a dose goes to the pharmacy, ships and is delivered.
How do refills and subscriptions work?
When a provider approves a treatment plan it renews on its own schedule. Before each renewal the patient gets an email with the date, the amount and a link to pause or cancel. You choose how many days ahead it goes out, from 1 to 14.
The card is only charged once a provider has approved. A declined request releases the hold.
Do you help with LegitScript certification?
Yes. MDside is LegitScript certified and has a partnership with LegitScript, so your application is prepared against the same pieces LegitScript reviews: the professional entity, the pharmacies, the labs and the protocols.
The decision and its timing stay with LegitScript. Nobody can promise you a certification date.
Do I need my own professional corporation in every state?
Not always, and the answer turns on where your patients are rather than where your company is. Some states require a domestic professional entity, some accept a foreign qualification, and some regulate the physician rather than the company. It is a decision sequence. See do you need a separate PC in every state.
What is a white-label telehealth platform?
Software that puts an operator's brand on the front of a telehealth offering: a storefront, an intake, a way to take payment and a way to reach a clinician. The brand on the site belongs to the operator. The care is rendered by licensed providers through a professional entity, and the infrastructure belongs to the vendor.
What varies enormously is how much of the clinical side comes with it. Some supply software only. Some add a provider network. Far fewer supply the medical direction and the professional entity that make the encounter defensible.
You can assemble this from two vendors and find the seam later, or you can look at one chain on one call.
Bring your menu and your target states. You will leave with a read on which states open first and what sits between you and selling in them, whether or not you end up working with us.
Book an intro callThis is general information, not legal advice. Rules vary by state and change. Confirm your own facts with counsel.
MDside, 401 E Jackson St, Ste 2340, Tampa, FL 33602.